
It's one of the most consequential conversations in dentistry, and it's often had too quickly. A tooth is heavily broken down. The X-ray shows bone loss, or a crack, or a previous root canal that's failed. And the question arrives: is it worth trying to save this, or should we take it out?
Here's how we actually work through that decision.
There Is No Universal Answer
The right answer depends on the specific tooth, the specific patient, and the specific circumstances — not on a general rule about what's worth saving and what isn't.
A tooth that looks hopeless on a routine periapical often reveals a different picture under a microscope with cone beam CT. A tooth that looks salvageable can be impossible to restore properly even if endodontic treatment succeeds. The clinical and the restorative picture have to be considered together, and one without the other leads to poor decisions in both directions.
What We're Actually Weighing
When we assess whether to save or extract, the questions we're asking are:
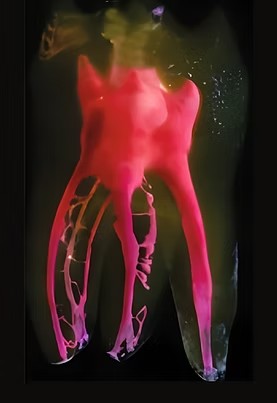
Can the root system be adequately treated? A tooth with calcified canals, a previous failed root canal, or a complex anatomy needs specialist assessment before that question can be answered with any confidence. A periapical alone isn't enough.
Is there enough tooth structure left to restore it properly? A root canal on a tooth that can't be crowned afterwards isn't a solution — it's a postponed extraction with extra steps. Ferrule effect matters. If there isn't enough tooth above the gum line to support a proper restoration, the endodontic prognosis is irrelevant.
What's the periodontal situation? A tooth with significant bone loss around the root is a different case to a tooth with a healthy periodontium. If the support structure is compromised, even technically excellent endodontic treatment won't produce a long-term result.
What does the patient want? This is underweighted in a lot of clinical discussions. A patient who wants to keep their tooth and understands the prognosis, the cost, and the realistic odds deserves the opportunity to make that choice. A patient who would rather have certainty and move on to an implant deserves that conversation equally honestly.
When the Maths Points to Extraction
Root canal treatment on a tooth with a poor prognosis — heavily compromised, previously retreated, uncertain restorability — can cost upwards of £1,500. If the realistic chance of long-term success is fifty percent or less, that's a significant sum for an uncertain outcome.
An implant placed by a specialist on a well-prepared site with good bone volume has a significantly better long-term success rate. When the numbers and the prognosis point that way, we say so plainly. The goal is the right outcome for the patient — not the maximum number of procedures on the way there.
When We Push Hard to Save the Tooth
Before any extraction conversation, we want to know that the decision is being made with full information. That means a proper assessment under magnification, not just a clinical look and a periapical. A cone beam CT where the anatomy is uncertain or where previous treatment has been placed. A clear understanding of what restoration is planned if endodontic treatment succeeds.
A tooth that gets extracted because it "looked too far gone" on a two-dimensional X-ray, without anyone looking at it properly in three dimensions, is a tooth that may have been lost unnecessarily.
We'd rather spend time on the assessment and reach the right answer than move quickly to a decision that can't be undone.
The Conversation We Always Have
Whatever the clinical picture, we explain it clearly before anything is decided. What the tooth looks like. What treatment would involve. What the realistic prognosis is. What the alternatives are, and what they cost. You make the final decision with that information in front of you.
No surprises after the fact. No treatment agreed to under pressure. Just an honest picture, and then a plan.